
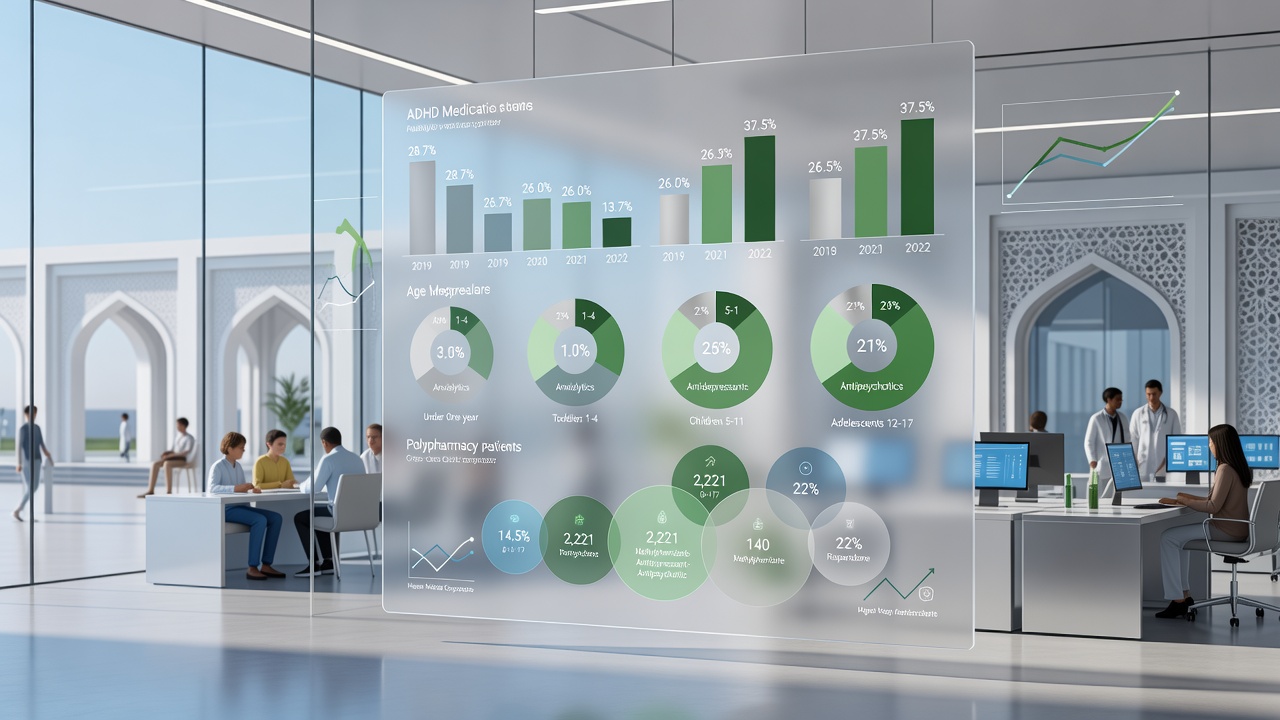
A retrospective review of public health records in Qatar found that nearly 15 percent of children and adolescents prescribed psychotropic medications between 2019 and 2022 had drugs from more than one medication class recorded in their files. The analysis, published in Frontiers in Psychiatry, also documents a marked shift in prescribing patterns over the four-year period, with anxiety medications rising sharply as attention-deficit/hyperactivity disorder (ADHD) drugs declined as a share of total prescriptions.
What the records show
Researchers examined 2,941 psychotropic prescriptions for 2,221 patients aged 0 to 17, drawn from the shared electronic health record system of Hamad Medical Corporation and the Primary Health Care Corporation-the two providers covering roughly 90 percent of Qatar's population. Prescriptions were sorted into five categories: antidepressants, antipsychotics, anxiolytics, mood stabilizers, and ADHD medications. Between 2019 and 2022, the ADHD medication share fell from 28.7 percent to 13.7 percent of records, while anxiolytics rose from 26.0 percent to 37.5 percent. Antidepressant prescribing peaked at 26.5 percent in 2021.
Patterns varied substantially by age. Every eligible prescription for infants under one year fell into the anxiolytic category, a group that also dominated prescriptions for toddlers aged 1 to 4. ADHD medications were most common among children aged 5 to 11, while antidepressants and antipsychotics together accounted for roughly two-thirds of prescriptions among adolescents aged 12 to 17. The authors note that some anxiolytic and mood-stabilizer drugs, including certain antiepileptic agents and benzodiazepines, are often prescribed for neurological conditions such as seizure disorders rather than psychiatric diagnoses-a distinction reflected in the data, since nearly 80 percent of seizure-linked prescriptions fell under the anxiolytic label.
Measuring overlapping prescriptions
The study's central safety measure, termed "potential cross-class polypharmacy," counted patients with medications from two or more classes recorded at any point during the study window. Of 2,221 patients, 322-about 14.5 percent-met this threshold, with the proportion climbing steadily by age group, from under 2 percent among 1- to 4-year-olds to nearly 22 percent among adolescents. A gender-adjusted statistical model found each additional year of age raised the odds of meeting the criterion.
The most frequently recorded class pairing was antidepressant-antipsychotic, found in 140 patients, followed by ADHD medication-antipsychotic in 75 patients. At the individual-drug level, methylphenidate paired with risperidone was the most common combination. Risperidone, an antipsychotic, appeared repeatedly across frequent pairings, which the authors flagged as a possible priority for closer monitoring given known metabolic, cardiovascular, and sedative risks associated with antipsychotic use in young patients.
Important caveats on interpretation
The authors stressed that their polypharmacy measure does not confirm patients took multiple drugs simultaneously. The dataset lacked sufficient detail to reconstruct continuous treatment timelines, making it impossible to distinguish concurrent use from sequential prescribing or medication switching. A sensitivity analysis excluding patients with seizure disorders or cerebral palsy raised the overlap rate slightly, to nearly 17 percent, suggesting the core patterns were not driven primarily by neurological prescribing.
The findings apply only to Qatar's public healthcare system and do not capture private-sector treatment or care received abroad. The researchers describe the results as identifying candidates for structured medication review, particularly among adolescents and patients with antipsychotic prescriptions, rather than as evidence of inappropriate care. They called for future studies incorporating verified treatment duration and clinical outcomes to clarify whether overlapping prescriptions reflect genuine concurrent treatment.